Heart failure remains one of the leading causes of hospitalization, disability, and mortality worldwide. Although many people associate heart failure with...
Heart failure remains one of the leading causes of hospitalization, disability, and mortality worldwide. Although many people associate heart failure with a weakened heart muscle that cannot pump blood effectively, not all heart failure cases involve reduced pumping function. A significant proportion of patients experience a condition known as diastolic congestive heart failure, also referred to as Heart Failure with Preserved Ejection Fraction (HFpEF).
Key takeaways
Diastolic congestive heart failure (HFpEF) involves impaired ventricular relaxation with preserved ejection fraction leading to elevated filling pressures and congestion.
Use specific ICD-10 codes I50.30 through I50.33 to document unspecified, acute, chronic, and acute on chronic diastolic heart failure.
Echocardiography and BNP or NT-proBNP testing are essential to confirm diastolic dysfunction, preserved EF, and elevated filling pressures.
Management focuses on symptom relief and comorbidity control: diuretics, blood pressure control, SGLT2 inhibitors, lifestyle measures, and tailored rehabilitation.
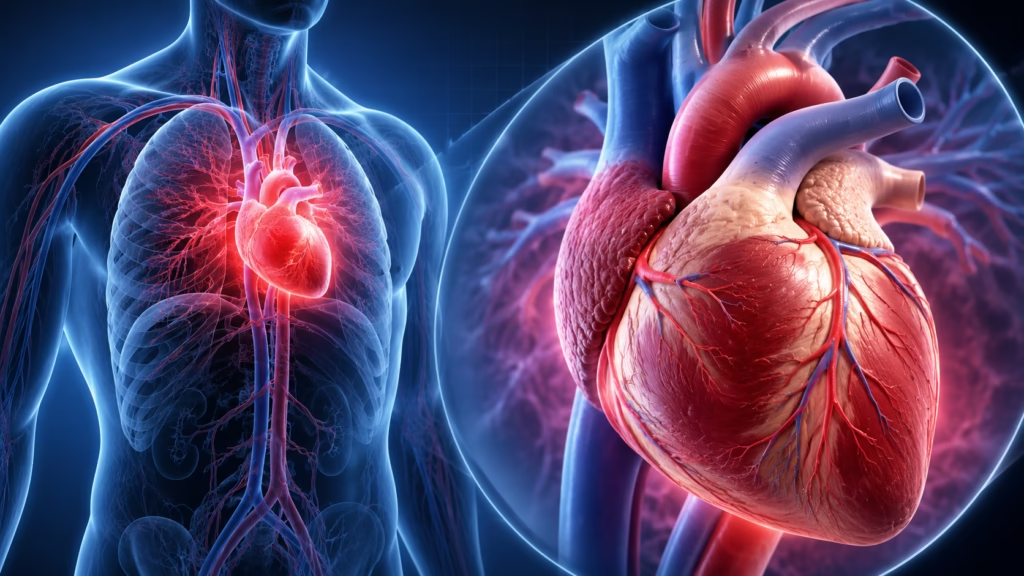
In diastolic heart failure, the heart’s pumping ability often remains relatively normal. However, the heart muscle becomes stiff and less flexible, making it difficult for the ventricles to relax and fill properly with blood during the resting phase of the cardiac cycle. This impaired filling leads to increased pressure within the heart and lungs, causing symptoms such as shortness of breath, fatigue, and fluid retention.
As the prevalence of hypertension, diabetes, obesity, and aging populations continues to rise globally, the number of patients diagnosed with HFpEF has increased substantially. Consequently, accurate diagnosis, documentation, and ICD-10 coding have become increasingly important.
This comprehensive guide explores diastolic congestive heart failure, its causes, symptoms, diagnostic criteria, treatment approaches, and the ICD-10 codes used to document the condition accurately.
Understanding Diastolic Congestive Heart Failure
What Is Diastolic Congestive Heart Failure?
Diastolic congestive heart failure is a form of heart failure in which the heart muscle loses its ability to relax normally during diastole, the phase of the cardiac cycle when the heart fills with blood.
Under normal conditions, the left ventricle relaxes between heartbeats and fills efficiently with oxygen-rich blood before pumping it throughout the body.
In patients with diastolic heart failure:
The ventricular muscle becomes stiff.
The ventricle cannot relax properly.
Filling pressures increase.
Less blood enters the ventricle during diastole.
Blood backs up into the lungs and circulation.
As a result, patients develop symptoms of congestion despite having relatively preserved pumping function.
Why Is It Called Heart Failure with Preserved Ejection Fraction (HFpEF)?
Ejection fraction (EF) measures the percentage of blood pumped out of the left ventricle with each heartbeat.
A normal ejection fraction is generally considered:
55% to 70%
In diastolic heart failure, the ejection fraction is usually:
50% or higher
Because pumping function remains relatively preserved, the condition is referred to as Heart Failure with Preserved Ejection Fraction (HFpEF).
This distinguishes it from Heart Failure with Reduced Ejection Fraction (HFrEF), where the heart’s pumping ability is significantly impaired.
Understanding the Pathophysiology
Ventricular Stiffness
One of the hallmark features of diastolic heart failure is ventricular stiffness.
Over time, conditions such as hypertension and aging can cause thickening and fibrosis of the heart muscle.
This stiffened muscle cannot expand normally during filling.
Reduced Chamber Compliance
Compliance refers to the ability of the ventricle to stretch and accommodate incoming blood.
In HFpEF:
The ventricle becomes less compliant.
Filling requires higher pressures.
Blood flow becomes restricted.
Elevated Left Atrial Pressure
Because the left ventricle resists filling, pressure builds up in the left atrium.
The increased pressure is transmitted backward into the pulmonary circulation.
Pulmonary Congestion
Elevated pressure within the pulmonary vessels causes fluid leakage into lung tissues.
This leads to symptoms such as:
Shortness of breath
Exercise intolerance
Orthopnea
Pulmonary edema
Common Risk Factors for Diastolic Heart Failure
Several conditions increase the likelihood of developing HFpEF.
Most guidelines recommend limiting sodium intake to:
2 grams per day or less
Fluid Restriction
Some patients benefit from limiting fluid intake to approximately:
2 liters daily
The goal is to prevent worsening congestion.
Daily Weight Monitoring
Sudden weight gain often indicates fluid accumulation.
Patients should record their weight every morning.
Physical Activity
Moderate aerobic exercise can improve:
Functional capacity
Cardiovascular fitness
Quality of life
Exercise programs should be individualized.
Pharmacologic Therapy
Diuretics
Diuretics reduce fluid overload and relieve symptoms.
Common examples include:
Furosemide
Bumetanide
Torsemide
ACE Inhibitors and ARBs
These medications help:
Control blood pressure
Reduce cardiac workload
Improve cardiovascular outcomes
Beta-Blockers
Beta-blockers slow heart rate and reduce myocardial oxygen demand.
Mineralocorticoid Receptor Antagonists
Spironolactone may help reduce hospitalizations in selected HFpEF patients.
SGLT2 Inhibitors
Recent research has demonstrated benefits from medications such as:
Empagliflozin
Dapagliflozin
These drugs may improve outcomes in HFpEF regardless of diabetes status.
Advanced Therapies
Treating Coronary Artery Disease
Addressing ischemia can improve symptoms and outcomes.
Managing Arrhythmias
Atrial fibrillation frequently coexists with HFpEF and requires appropriate treatment.
Heart Failure Clinics
Specialized clinics provide multidisciplinary management and monitoring.
Cardiac Rehabilitation
Structured rehabilitation programs improve exercise capacity and quality of life.
Documentation Best Practices
Clearly Document Heart Failure Type
Always specify:
Diastolic
Systolic
Combined
Document Acuity
Providers should clearly indicate whether the condition is:
Acute
Chronic
Acute on chronic
Include Ejection Fraction
Recording the EF supports diagnostic specificity.
Document Diagnostic Findings
Include:
BNP levels
Echocardiogram findings
Diastolic dysfunction grade
Capture Comorbidities
Important comorbid conditions include:
Hypertension
Diabetes
Obesity
Chronic kidney disease
Coronary artery disease
Common Coding Pitfalls
Using I50.9 Unnecessarily
Avoid unspecified codes when documentation provides greater detail.
Missing Acuity
Failure to identify acute versus chronic status may result in incorrect coding.
Omitting Contributing Conditions
Underlying causes and associated conditions should be documented whenever present.
Why Accurate Coding Matters
Appropriate Reimbursement
Heart failure management is complex and resource intensive.
Accurate coding ensures appropriate compensation for services provided.
Research and Public Health
Specific coding helps researchers understand disease prevalence and outcomes.
Quality Reporting
Healthcare organizations rely on coding data for performance measurement.
Improved Care Coordination
Clear documentation supports communication among:
Physicians
Nurses
Coders
Specialists
Care managers
Conclusion
Diastolic congestive heart failure, also known as Heart Failure with Preserved Ejection Fraction (HFpEF), is a complex and increasingly common form of heart failure. Although the heart’s pumping ability remains relatively preserved, impaired ventricular relaxation leads to elevated filling pressures, congestion, and significant symptoms that can greatly affect quality of life.
Accurate ICD-10 coding is essential for capturing the severity and complexity of the condition. Codes ranging from I50.30 through I50.33 allow clinicians and coders to distinguish between unspecified, acute, chronic, and acute-on-chronic forms of diastolic heart failure. Proper documentation of heart failure type, acuity, ejection fraction, diagnostic findings, and associated comorbidities ensures accurate reimbursement, enhances patient care, supports research efforts, and strengthens healthcare quality reporting.
By combining strong clinical documentation with precise ICD-10 coding practices, healthcare professionals can improve outcomes for patients living with this challenging cardiovascular condition while supporting efficient and effective healthcare delivery.
Disclaimer
This article is for educational purposes only and does not replace professional medical advice, diagnosis, or treatment. Seizures, severe headache, confusion, visual changes, or blood pressure readings in the hypertensive crisis range require urgent medical evaluation.
Thank you! Your feedback helps us improve our articles.
True Impact Health articles are written by our editorial team and based on reliable sources such as public health agencies, clinical guidelines and peer-reviewed research. This article has not yet been medically reviewed. Read our editorial process.
This content is for general information and is not a substitute for professional medical advice, diagnosis or treatment.