ICD 10 Code for Gestational Hypertension Third Trimester
Accurate medical coding is essential for healthcare documentation, reimbursement, regulatory compliance, and patient care. In obstetric medicine, proper...
Accurate medical coding is essential for healthcare documentation, reimbursement, regulatory compliance, and patient care. In obstetric medicine, proper coding becomes particularly important because pregnancy-related conditions often require close monitoring and can significantly affect both maternal and fetal outcomes.
Key takeaways
Use ICD-10-CM code O13.2 for gestational hypertension without significant proteinuria during the third trimester (weeks 28 through 42).
Assign O13.2 only when hypertension begins after 20 weeks, proteinuria is absent, and there is no evidence of preeclampsia.
Document gestational age, multiple elevated blood pressure readings, and laboratory proteinuria status to support accurate coding and reduce claim denials.
One commonly encountered pregnancy complication is gestational hypertension. This condition develops when a pregnant woman experiences elevated blood pressure after 20 weeks of gestation without evidence of significant proteinuria or other features of preeclampsia. Because gestational hypertension can increase the risk of serious complications if not properly managed, accurate diagnosis and coding are crucial.
For patients diagnosed with gestational hypertension during the third trimester, the correct ICD-10-CM code is O13.2. While identifying the code itself may seem straightforward, understanding when it should be used, how it differs from other pregnancy-related hypertension codes, and what documentation is required is equally important.
This comprehensive guide explains the clinical meaning of gestational hypertension, the structure of ICD-10 pregnancy-related hypertension codes, proper use of O13.2, documentation requirements, and the importance of coding accuracy in modern healthcare.
Understanding Gestational Hypertension
What Is Gestational Hypertension?
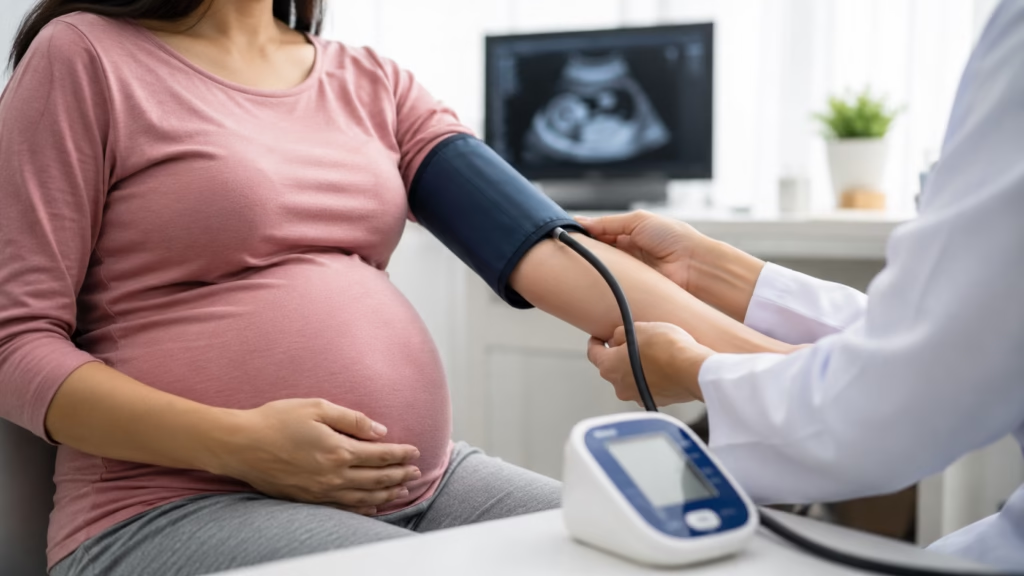
Gestational hypertension is a condition characterized by elevated blood pressure that develops during pregnancy after 20 weeks of gestation in a woman who previously had normal blood pressure.
Blood pressure is considered elevated when readings reach or exceed 140/90 mm Hg on at least two separate measurements taken several hours apart.
Unlike preeclampsia, gestational hypertension occurs without significant proteinuria, which refers to excessive protein levels in the urine. The absence of proteinuria is one of the key features that distinguishes gestational hypertension from more severe hypertensive disorders of pregnancy.
Although gestational hypertension may initially appear relatively mild, it should never be ignored because it can progress to preeclampsia, eclampsia, placental complications, or preterm delivery if not properly monitored.
Why Does Gestational Hypertension Develop?
The exact cause of gestational hypertension remains incompletely understood. Researchers believe the condition results from complex interactions involving:
Placental development
Maternal blood vessels
Hormonal changes
Immune system responses
Genetic factors
Pregnancy places increased demands on the cardiovascular system. In some women, these physiological changes contribute to elevated blood pressure during the second half of pregnancy.
Who Is at Higher Risk?
Several factors increase the likelihood of developing gestational hypertension.
Understanding these risk factors helps clinicians identify patients who may require closer monitoring.
Why Gestational Hypertension Matters
Impact on Maternal Health
Gestational hypertension is more than simply elevated blood pressure. If left unmanaged, it can affect multiple organ systems and increase the risk of serious pregnancy complications.
Potential maternal complications include:
Progression to preeclampsia
Placental abruption
Stroke
Kidney dysfunction
Liver complications
Seizures in severe cases
Early recognition and management are therefore essential for protecting maternal health.
Impact on the Baby
Gestational hypertension can also affect fetal development.
Elevated maternal blood pressure may reduce blood flow to the placenta, limiting oxygen and nutrient delivery to the developing baby.
Potential fetal complications include:
Restricted fetal growth
Low birth weight
Preterm birth
Fetal distress
Increased risk of neonatal intensive care admission
Because of these risks, healthcare providers often increase prenatal surveillance once gestational hypertension is diagnosed.
Prevalence of Gestational Hypertension
Gestational hypertension affects approximately 6% to 8% of pregnancies worldwide, making it one of the most common medical complications encountered during pregnancy.
Its frequency underscores the importance of accurate diagnosis, documentation, and coding.
Understanding ICD-10 Coding for Hypertensive Disorders in Pregnancy
What Is ICD-10-CM?
The International Classification of Diseases, Tenth Revision, Clinical Modification (ICD-10-CM) is the coding system used throughout the United States and many other healthcare systems to classify diagnoses and medical conditions.
ICD-10 codes serve several purposes:
Supporting reimbursement
Tracking disease prevalence
Facilitating research
Improving healthcare planning
Maintaining accurate patient records
Accurate coding ensures that patient encounters are properly documented and communicated across healthcare settings.
Pregnancy-Related Hypertension Codes
Pregnancy-related hypertension codes are located within Chapter 15 of ICD-10-CM, which covers:
Pregnancy, Childbirth, and the Puerperium (O00–O99).
Within this chapter, several code categories address hypertensive disorders.
This category is used when hypertension existed before pregnancy or developed before 20 weeks of gestation.
Because the hypertension predates the pregnancy, these cases are classified differently from gestational hypertension.
O11: Pre-Existing Hypertension with Superimposed Preeclampsia
This code category applies when a woman with chronic hypertension later develops preeclampsia during pregnancy.
These cases are generally considered higher risk and require careful monitoring.
O12 and O13: Gestational Edema, Proteinuria, and Hypertension
This category addresses hypertension that develops specifically during pregnancy without significant proteinuria.
Gestational hypertension falls within this group.
O14: Preeclampsia
Preeclampsia involves hypertension accompanied by proteinuria or signs of organ dysfunction.
Because it represents a more serious condition, separate coding is required.
O15: Eclampsia
Eclampsia refers to the development of seizures in a patient with preeclampsia.
This is considered a medical emergency and carries significant maternal and fetal risks.
ICD-10 Code O13.2 Explained
The Correct Code
For gestational hypertension without significant proteinuria occurring during the third trimester, the correct ICD-10-CM code is:
O13.2
Official Description
The official description is:
Gestational [pregnancy-induced] hypertension without significant proteinuria, third trimester.
This code specifically identifies patients who:
Develop hypertension after 20 weeks of gestation
Have no significant proteinuria
Are currently in the third trimester
Understanding the Trimester Breakdown
The O13 category is divided according to the stage of pregnancy.
O13.0 – First Trimester
Used when gestational hypertension occurs during the first trimester.
Although uncommon because gestational hypertension generally develops after 20 weeks, this code remains available for specific situations.
O13.1 – Second Trimester
Used when gestational hypertension is documented during the second trimester.
O13.2 – Third Trimester
Used when the condition is present during weeks 28 through 42 of pregnancy.
This is the code most commonly used because gestational hypertension frequently develops during late pregnancy.
O13.9 – Unspecified Trimester
Used only when documentation does not clearly identify the trimester.
Whenever possible, coders should avoid unspecified codes and select the most specific option available.
When Should O13.2 Be Used?
Elevated Blood Pressure After 20 Weeks
The patient must demonstrate elevated blood pressure readings that begin after 20 weeks of gestation.
This distinction is important because hypertension occurring before 20 weeks is generally classified as chronic hypertension rather than gestational hypertension.
Third Trimester Documentation
The medical record must indicate that the patient is in the third trimester.
This generally includes pregnancies between:
Week 28
Week 29
Week 30
Through delivery
Gestational age documentation helps support code selection.
Absence of Significant Proteinuria
One of the most important criteria for O13.2 is the absence of significant proteinuria.
Proteinuria suggests progression toward preeclampsia and would require a different code assignment.
Laboratory documentation should support this distinction.
No Evidence of Preeclampsia
O13.2 should not be assigned if the patient exhibits signs of preeclampsia.
Healthcare organizations use coded data to track pregnancy complications and evaluate maternal health trends.
Accurate coding contributes to research and healthcare planning efforts.
Enhanced Patient Care
Precise documentation and coding help clinicians monitor disease progression and make informed treatment decisions.
Conclusion
The correct ICD-10-CM code for gestational hypertension without significant proteinuria during the third trimester is O13.2. While the code itself is relatively straightforward, proper application requires a clear understanding of gestational hypertension, trimester classification, proteinuria status, and documentation requirements.
Accurate coding begins with thorough clinical documentation and careful review of the patient’s medical record. By ensuring that blood pressure findings, gestational age, and the absence of preeclampsia are clearly documented, healthcare professionals can confidently assign O13.2 and support accurate reimbursement, regulatory compliance, and high-quality patient care.
Whether you are a coder, biller, physician, nurse, or healthcare administrator, understanding when and how to use O13.2 is an essential part of effective obstetric documentation and coding practice.
Disclaimer
This article is for educational purposes only and does not replace professional medical advice, diagnosis, or treatment. Seizures, severe headache, confusion, visual changes, or blood pressure readings in the hypertensive crisis range require urgent medical evaluation.
Physician with experience in patient care and preventive medicine, focused on early detection, disease prevention and long-term wellness.
True Impact Health articles are written by our editorial team and based on reliable sources such as public health agencies, clinical guidelines and peer-reviewed research. This article has been checked by a doctor on our review panel. Read our editorial process.
This content is for general information and is not a substitute for professional medical advice, diagnosis or treatment.